The cancer-vaccine option: finance the evidence before counting the payment
Merck–Moderna’s collaboration provides the timeline; a separate cash model tests option exercise, delay, settlement and the no-payment branch.
Study design, endpoints, enrollment and the decisions supported by clinical evidence.

Merck–Moderna’s collaboration provides the timeline; a separate cash model tests option exercise, delay, settlement and the no-payment branch.

A patient-pathway funnel, starter-dose capacity check and financial threshold show why convenient dosing still needs an operating system.

Vyxeos provides the clinical anchor; a separate yield and cash-cost model tests whether a manufacturing improvement deserves investment.

FDA’s 2026 terminology change, a historical liver-chip benchmark and a transparent error-cost model show what a validation investment must establish.

A study visit at the kitchen table could remove a long journey. Good trial design also asks who gains access, who takes on new work, and how the evidence stays dependable.

A virtual counterpart makes an irresistible promise: explore possibilities before acting. Its usefulness depends on what it knows, what it leaves out, and how it earns trust.

A discovery becomes a medicine through thousands of repeatable decisions. Step inside the less visible world that turns a promising result into reliable supply.

A durable therapy changes more than a treatment schedule. It asks healthcare to think differently about follow-up, evidence, payment, and the years that come after.

AI can widen the search for a medicine. The more interesting question is how scientists decide which possibilities deserve to become experiments.

A result can move in the right direction while a person’s daily life remains difficult. Patient-reported outcomes help research ask more precisely what improvement means.

Living cells and carefully engineered channels offer a new window into human biology. The important question is which part of an organ a tiny model can faithfully represent.

A new antibiotic can be most valuable when it is used carefully. That creates a revealing challenge for how we fund discovery, protect effectiveness, and keep treatment available.

Follow the decisions between a promising result and completed care—and distinguish scientific failure from avoidable execution gaps.

A fictional day asks what earlier detection, personalized treatment, and connected care would need to deliver for a real person.
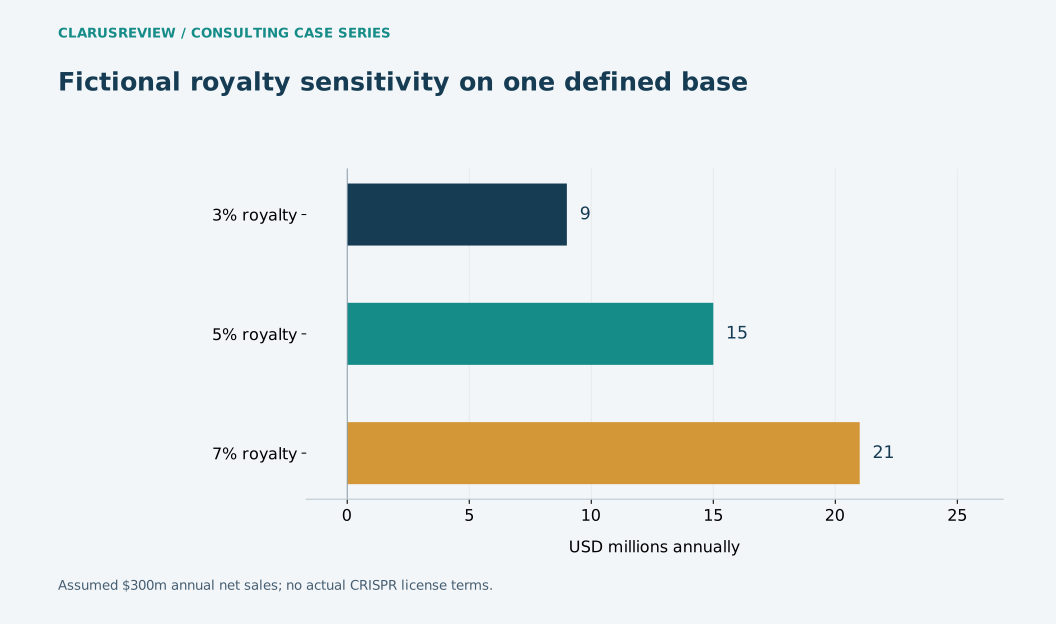
The CRISPR patent appeal frames a hypothetical rights map, licensing sensitivity and IP diligence gate.
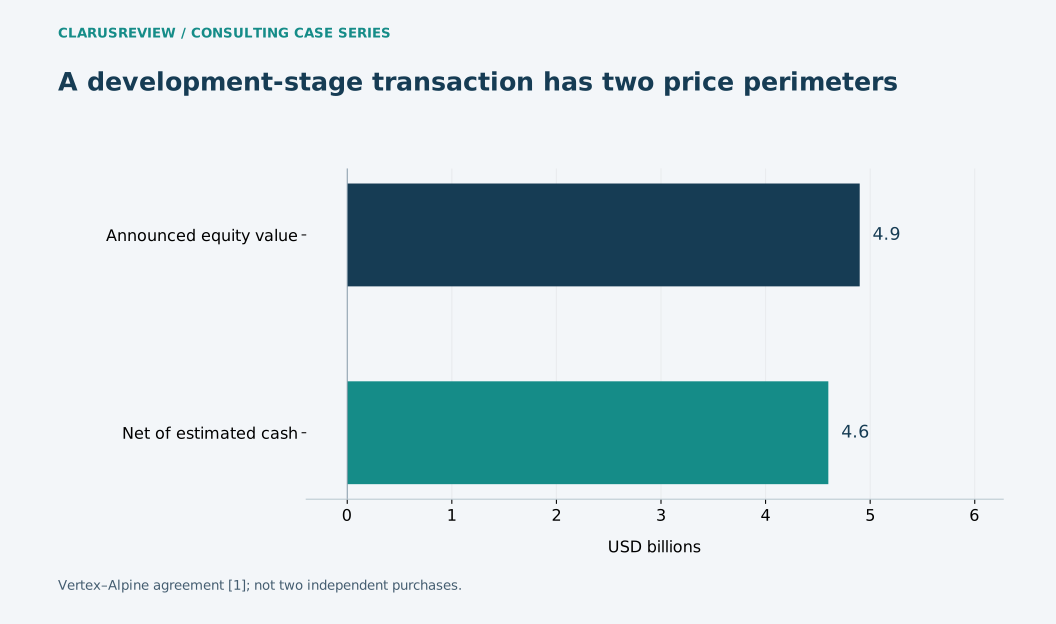
A development-stage acquisition and a company-reported upcoming review date frame a fictional option-value model.
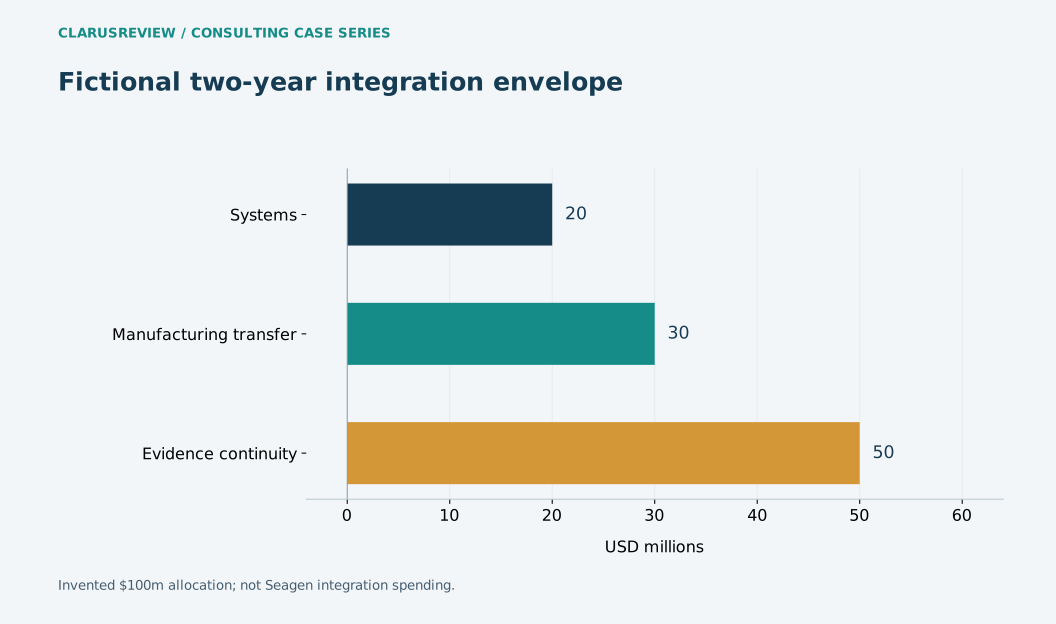
Pfizer–Seagen provides transaction context for a fictional buyer’s integration reserve and portfolio gates.
A major ADC collaboration and a recent filing setback frame staged licensing, dilution and evidence-linked funding.
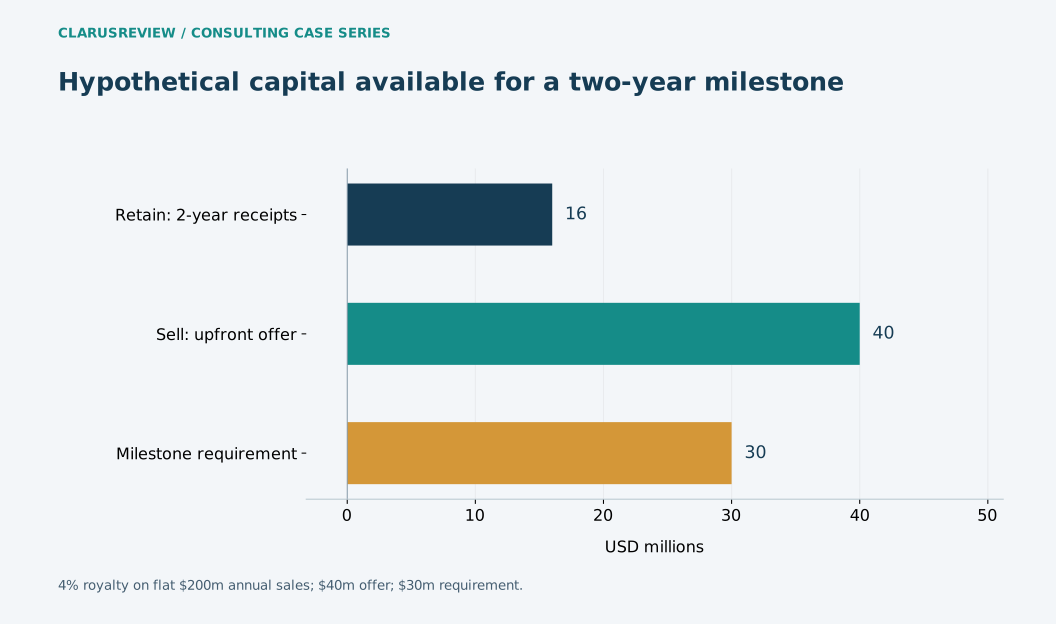
Cystic Fibrosis Foundation venture philanthropy frames a hypothetical royalty-retention and monetization decision.
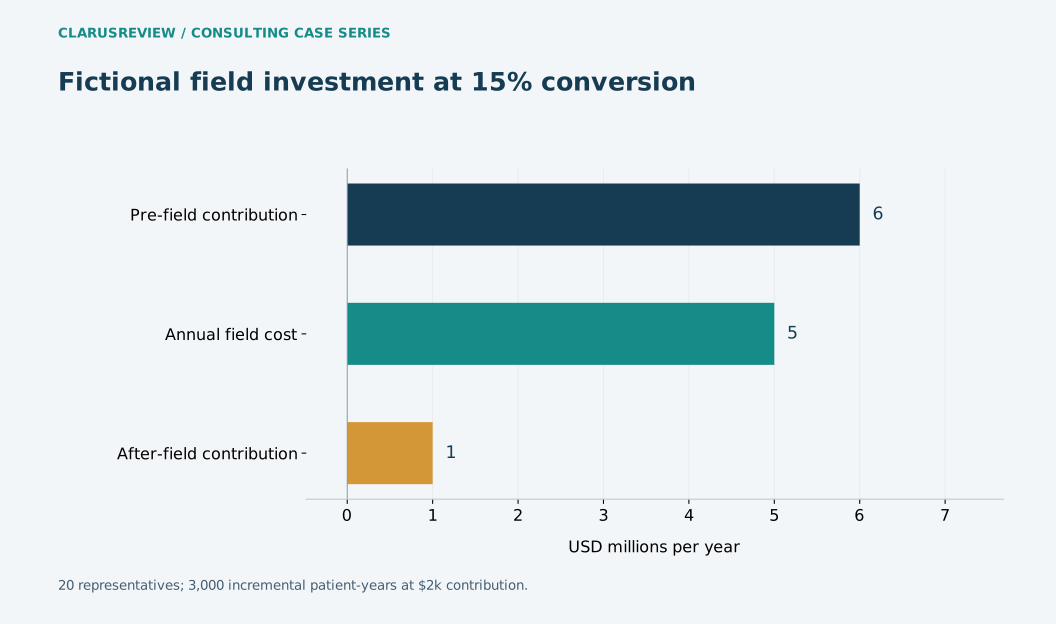
Recent generic-pressure reporting anchors a fictional sales-force redeployment and productivity model.
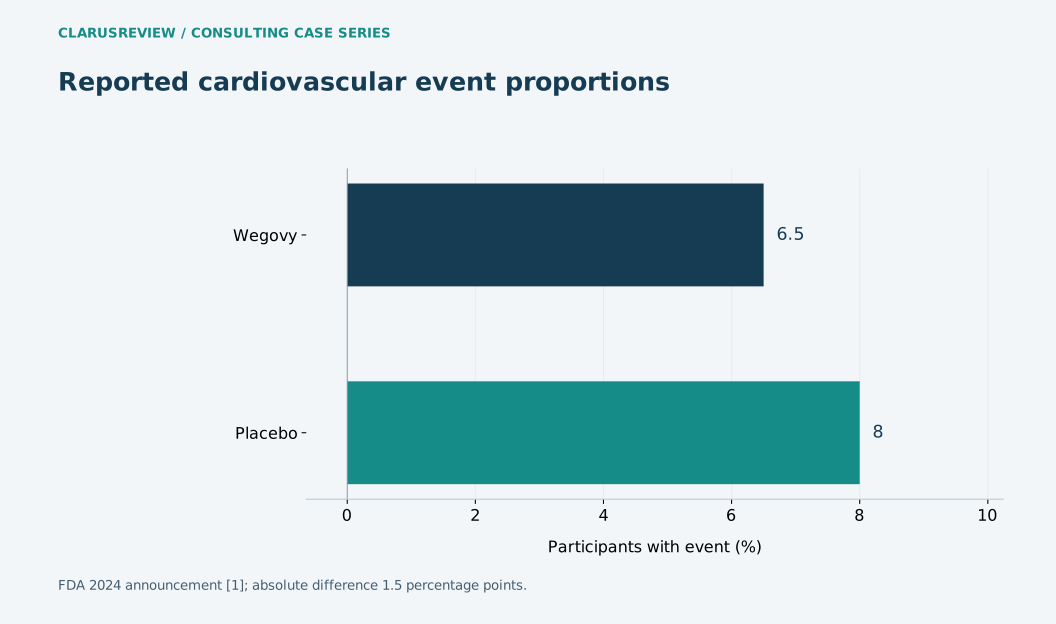
Wegovy’s outcomes result and Medicare’s next negotiation cycle frame evidence, budget and eligible-population planning.
Repatha’s historical reset and recent growth provide context for a fictional launch team’s break-even calculation.
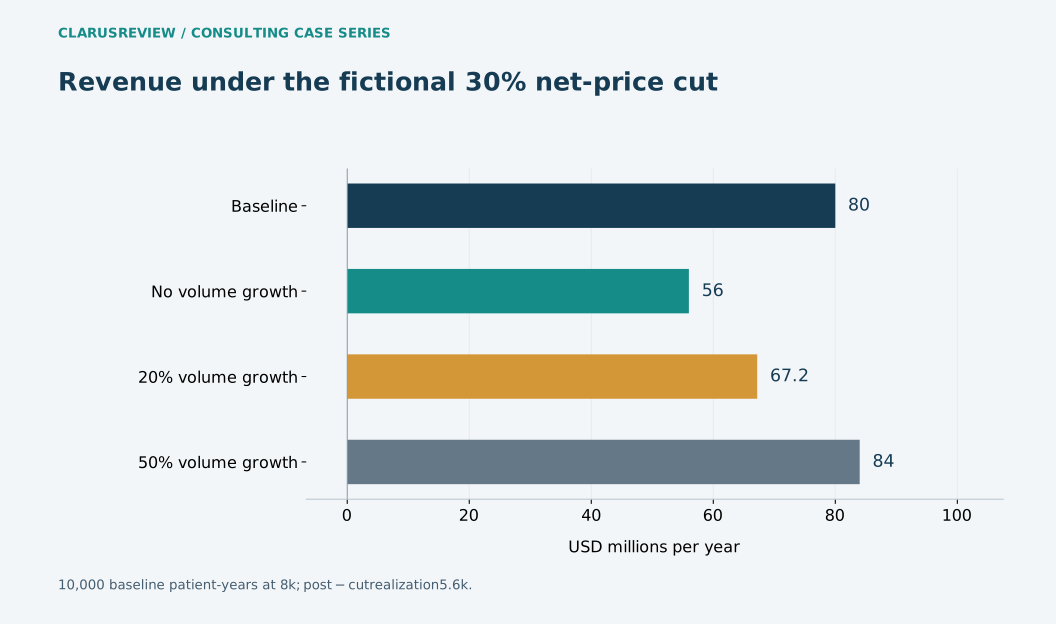
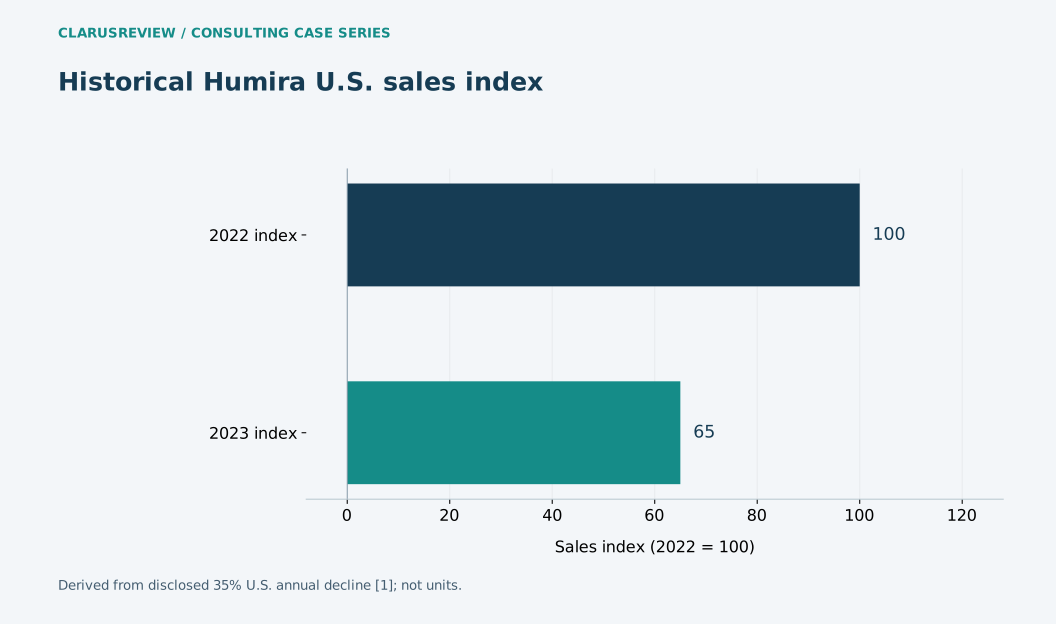
Historical U.S. erosion and 2026 global reporting inform a hypothetical biosimilar-response model.
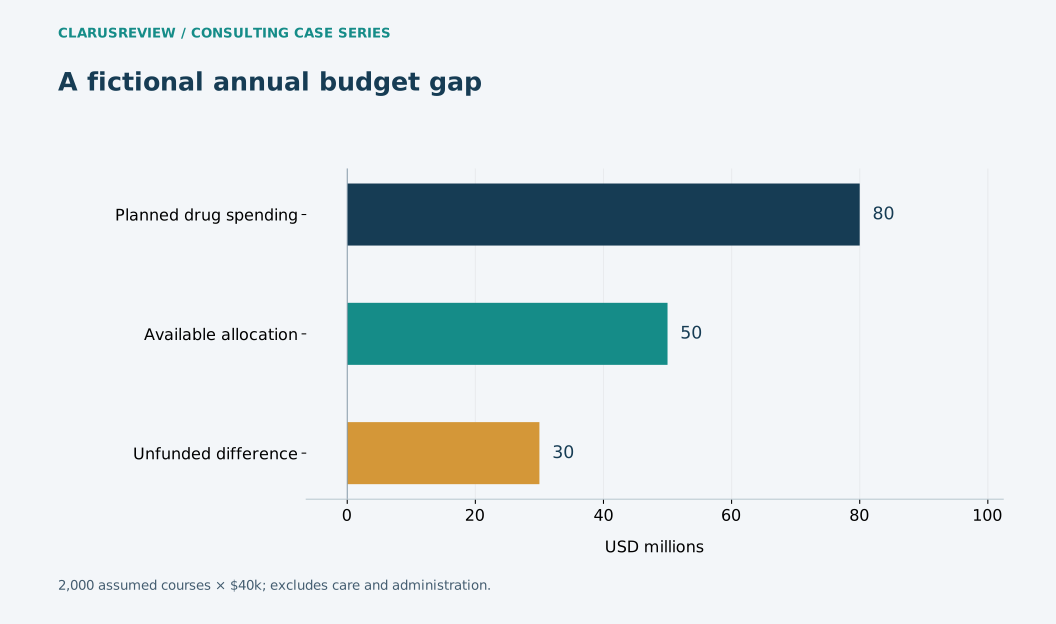
Sovaldi and current Medicare pricing implementation frame an indication-specific budget-impact assignment.
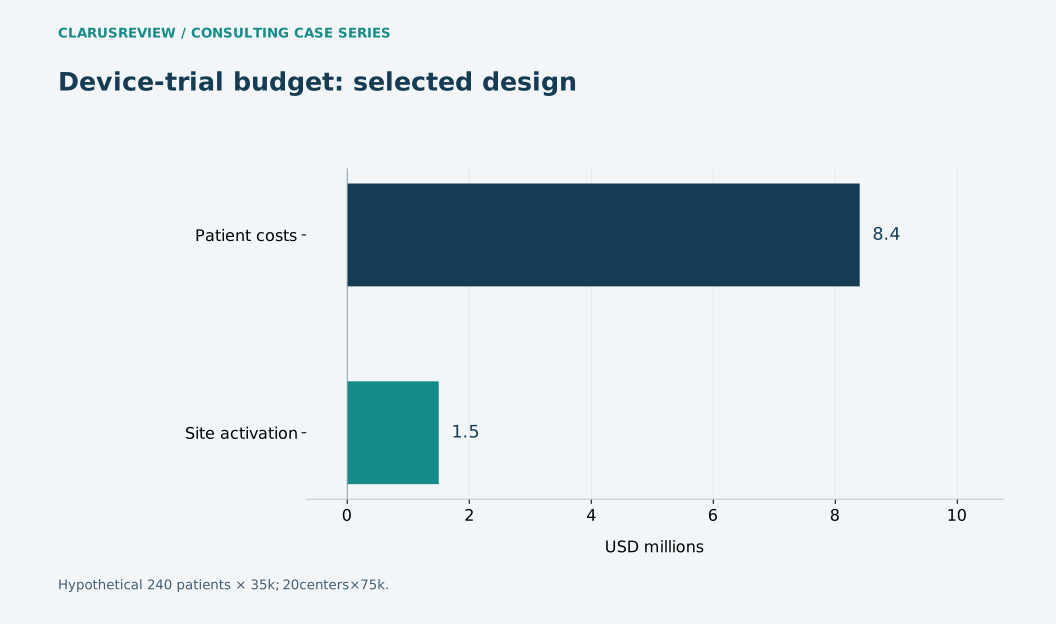
SYMPLICITY HTN-3 frames a hypothetical device trial budget, site plan and milestone gate.
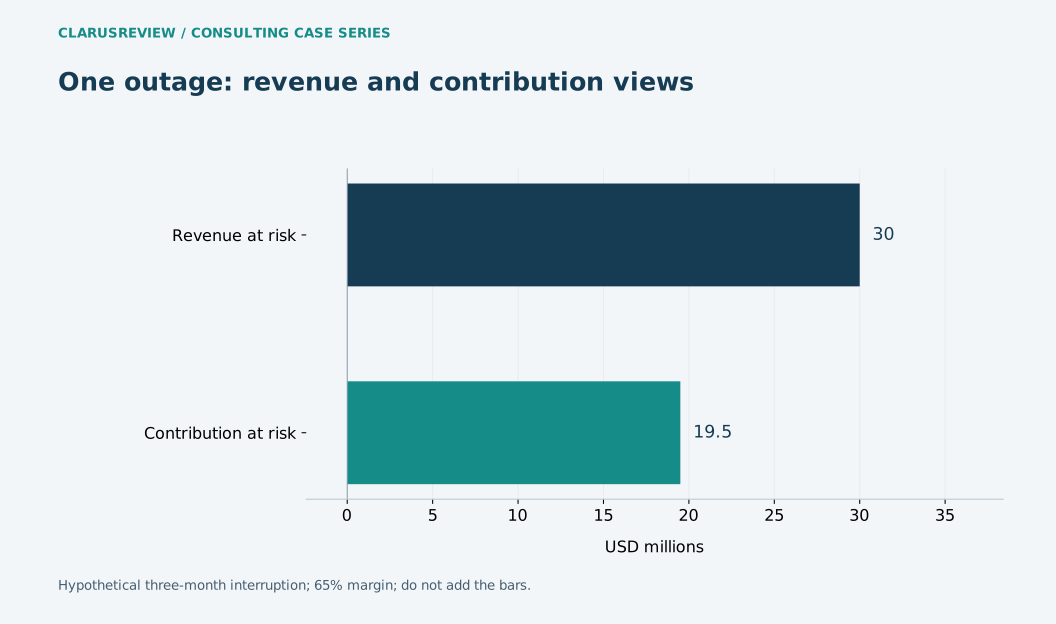
Genzyme’s remediation history anchors a hypothetical outage-exposure and backup-capacity decision.
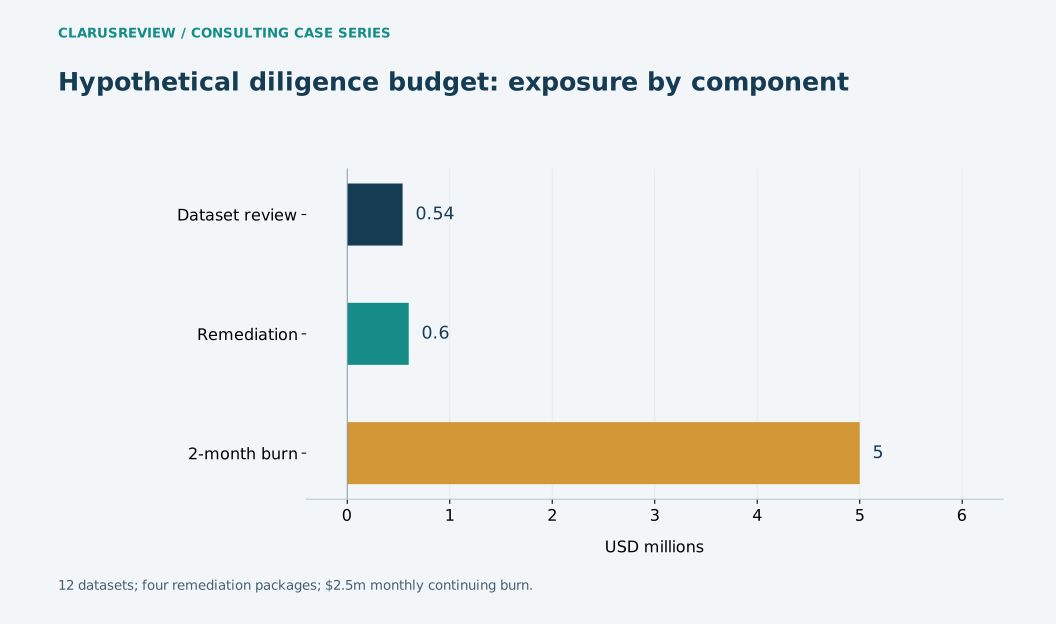
A historical gene-therapy data issue informs a hypothetical audit, remediation and transaction-delay model.
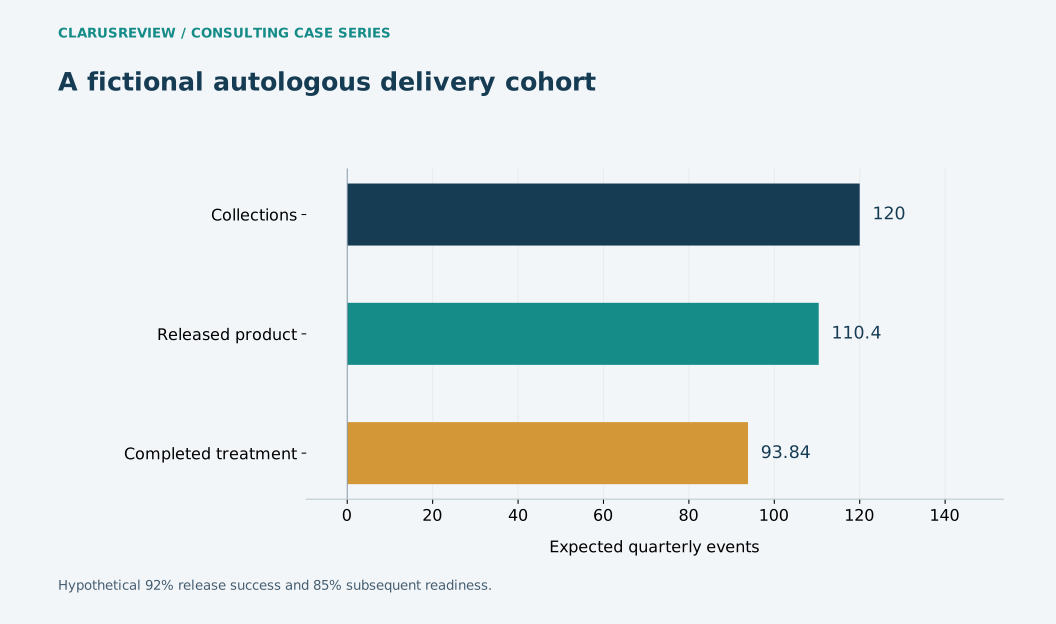
Kymriah and current cell-therapy commercialization frame manufacturing reliability, release timing and patient readiness.
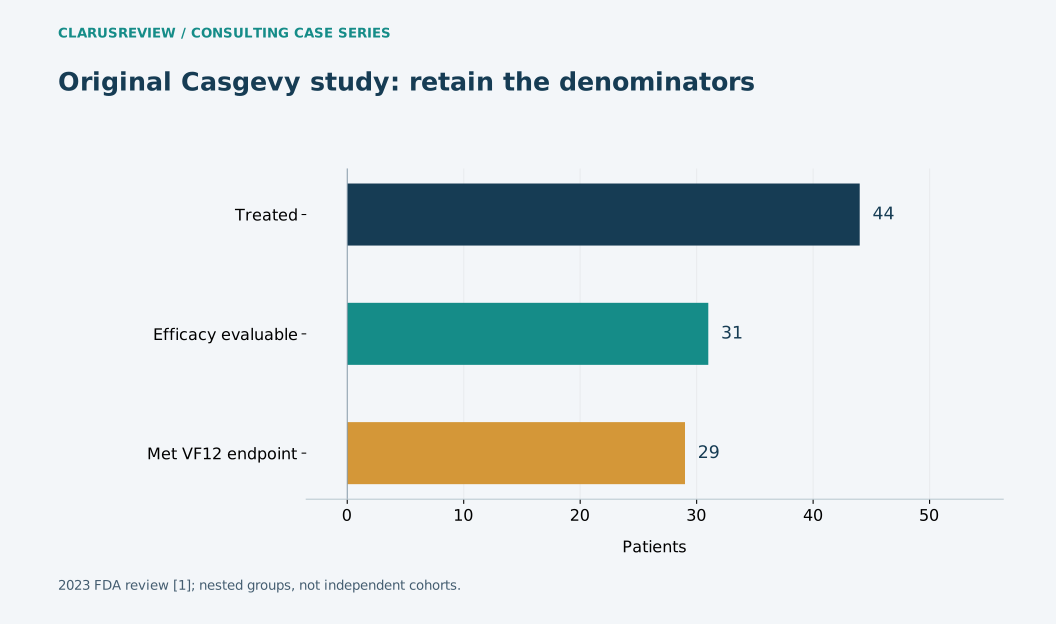
Original gene-editing evidence and 2026 launch revenue inform a hypothetical treatment-center capacity model.
The Elevidys safety revision informs a hypothetical surveillance budget and an eligibility-sensitive operating plan.
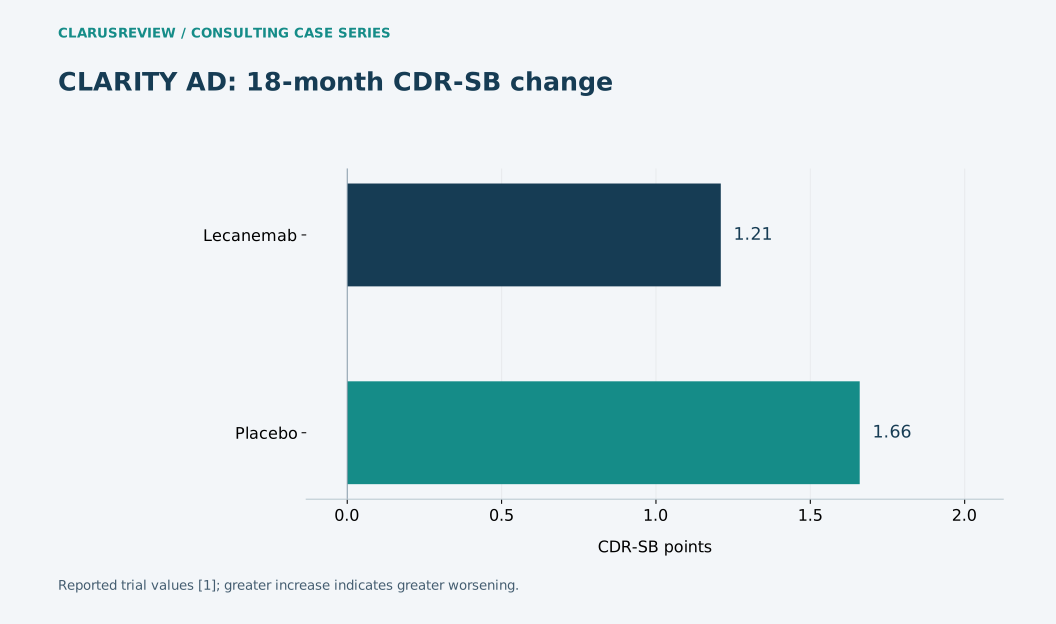
Leqembi’s randomized evidence and AMT-130’s September update frame a client’s sensitivity analysis and evidence reserve.
A September 2026 ADC filing withdrawal becomes a hypothetical evidence-gap, delay and cash-runway assignment.
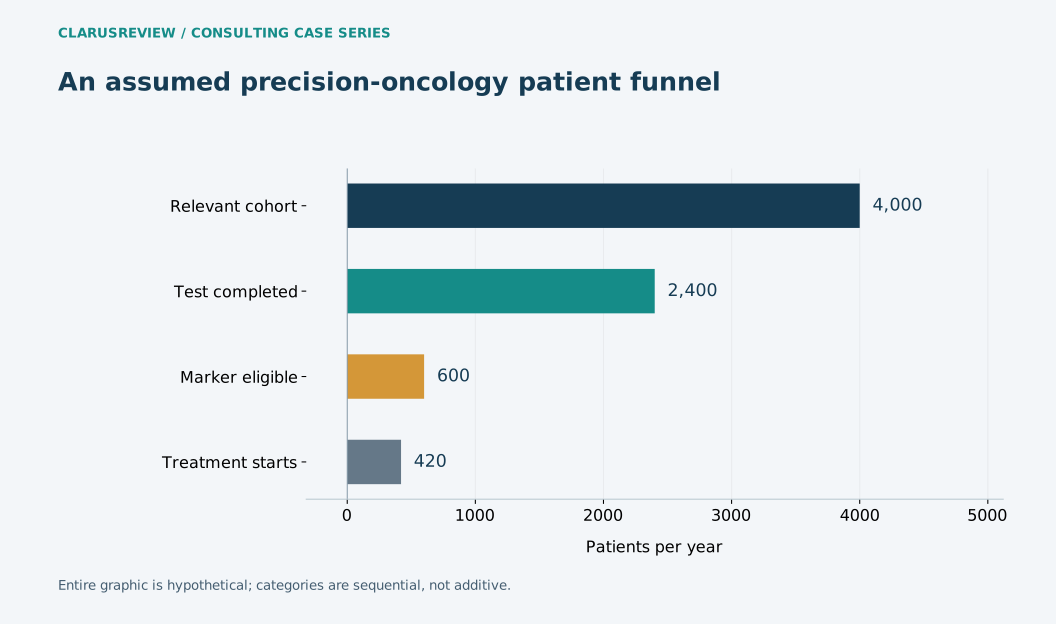
A drug–diagnostic operating model turns assay availability, testing attrition and turnaround into measurable launch dependencies.
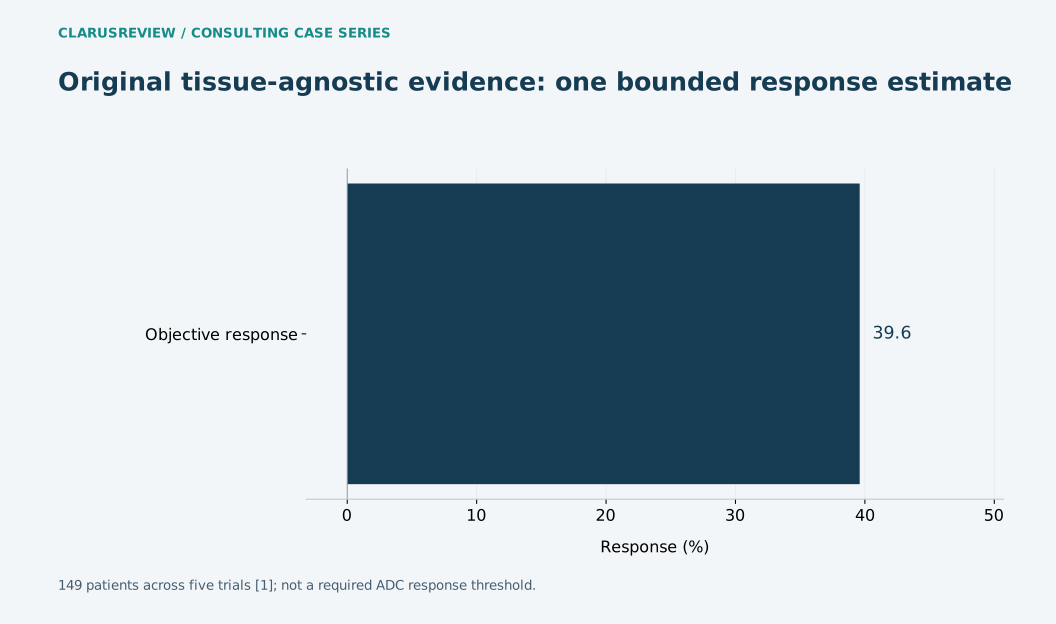
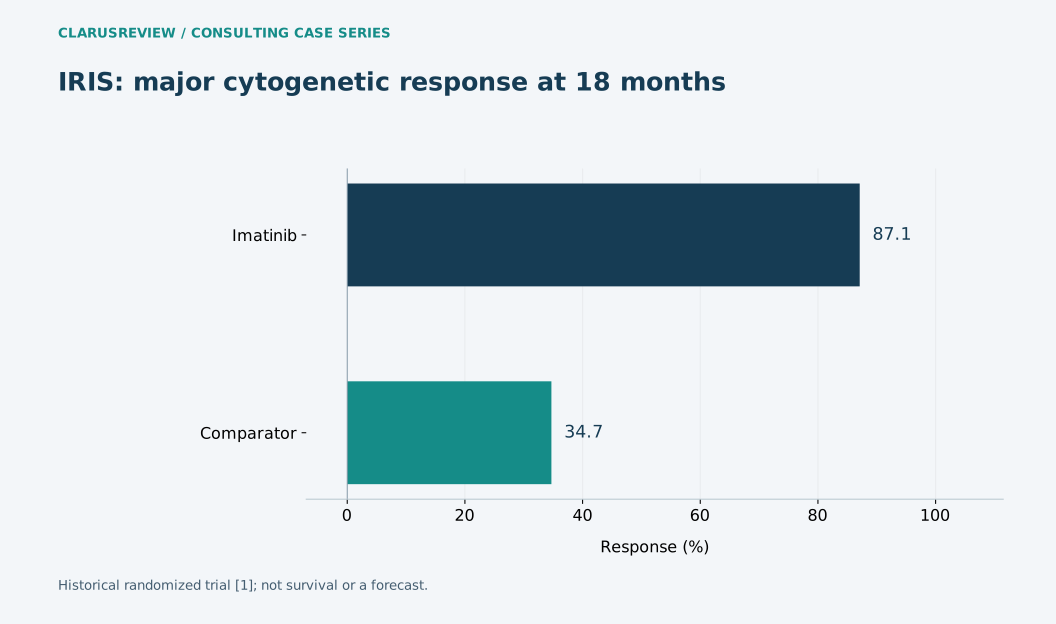
IRIS and a recent biomarker-led approval frame a hypothetical oncology program’s recruitment, assay and capital decisions.

Define the baseline, deliverables and economic perspective before attributing time or money saved to an intervention.

Coordinate clinical, regulatory and manufacturing decisions with clear ownership, acceptance criteria and measurable handoffs.

A numerical framework for understanding why a milestone may change value—and why the calendar alone does not.

Turn a leadership directory into a dated, evidence-based partnering process with measurable progression.

Historical financing events and a runway model clarify what a capital headline can—and cannot—tell a reader.

A practical architecture for communicating clinical meaning, financing exposure and the work required for adoption.

Sotatercept and OCEANIC-AF illustrate why a benefit claim must remain tied to its population, comparator and endpoint.

A MASH case shows why a biomarker result, an approval and a commercial forecast answer different questions.

Why a small, well-defined population still needs rigorous comparison, diagnostic execution and a clear financing plan.

Positive and negative trial examples show why endpoint choice, patient selection and execution costs must be assessed together.

Clinical endpoints, monitoring requirements and patient persistence belong in the same commercial plan.

A decision framework for separating clinical evidence, regulatory credibility and usable economic returns.
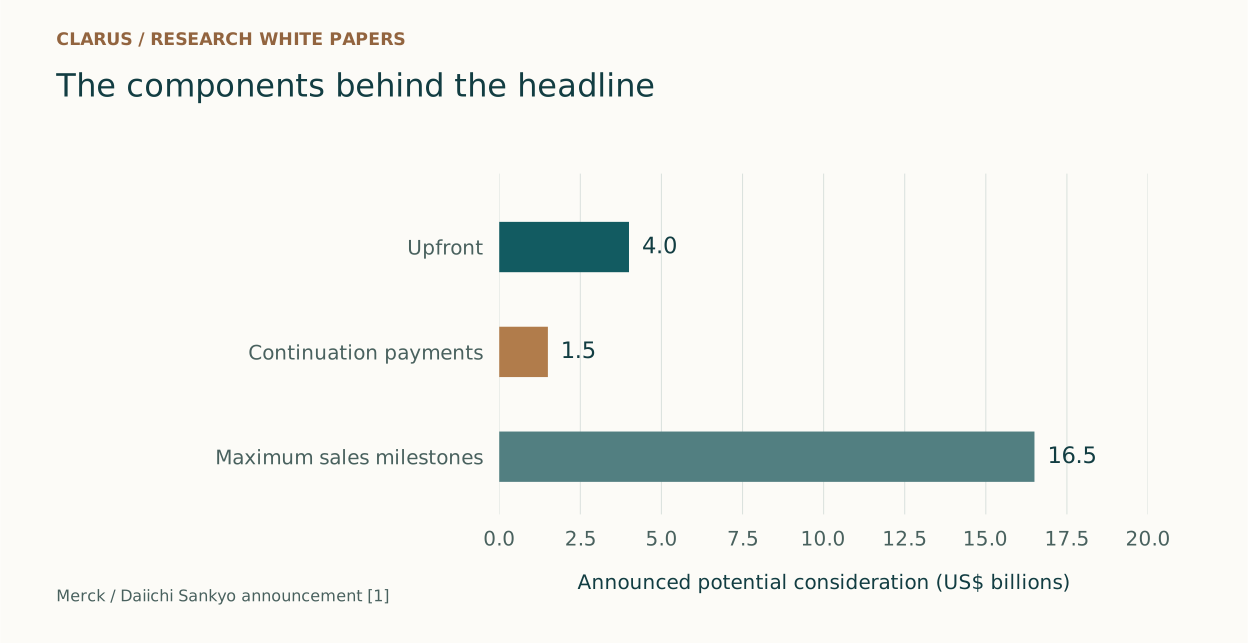
A large ADC collaboration illustrates why maximum announced consideration should be decomposed before it enters a value narrative.
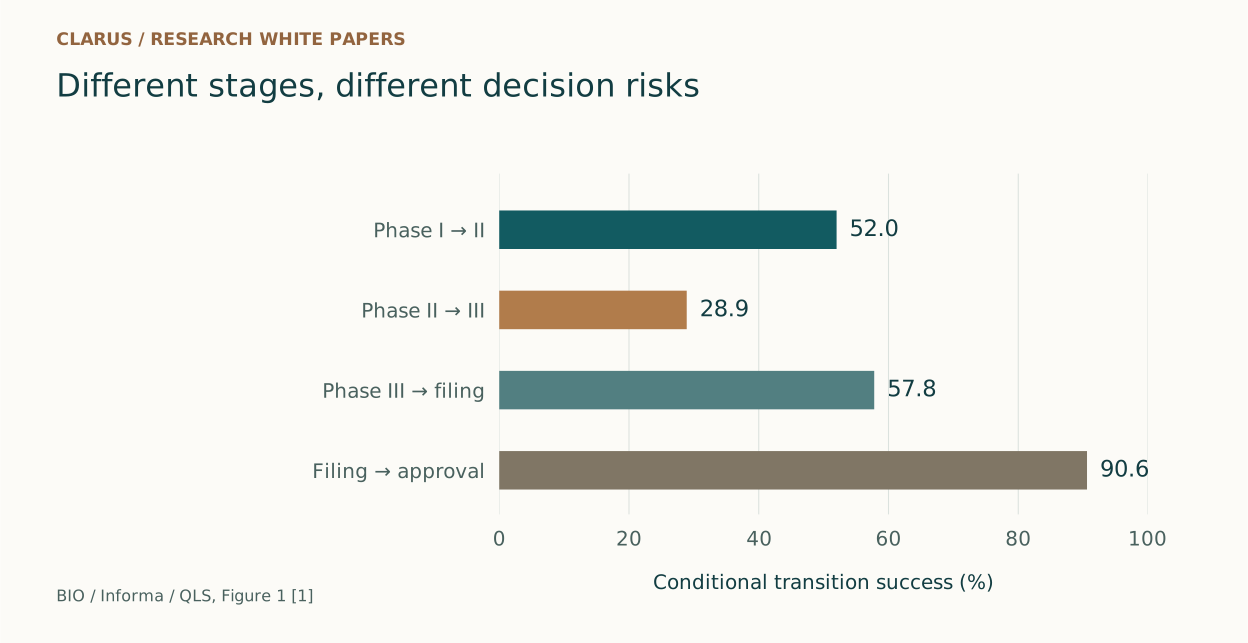
Historical transition rates help frame the challenge; the program’s evidence must determine the actual go, revise, or stop decision.

Recent FDA prevention counts provide a signal about supply interventions, while leaving product-level access questions unresolved.

A record approval year offers an opportunity to examine the operational steps between regulatory entry and patient access.
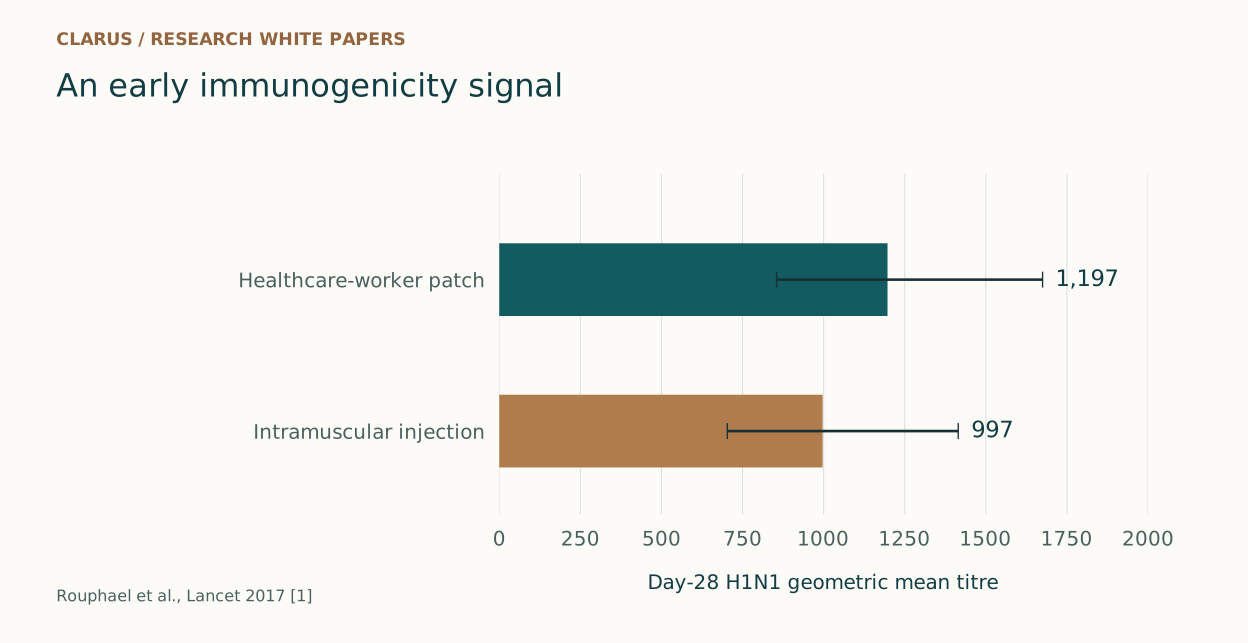
A small Phase I study provides a useful early signal and a clear boundary around what remains to be demonstrated.
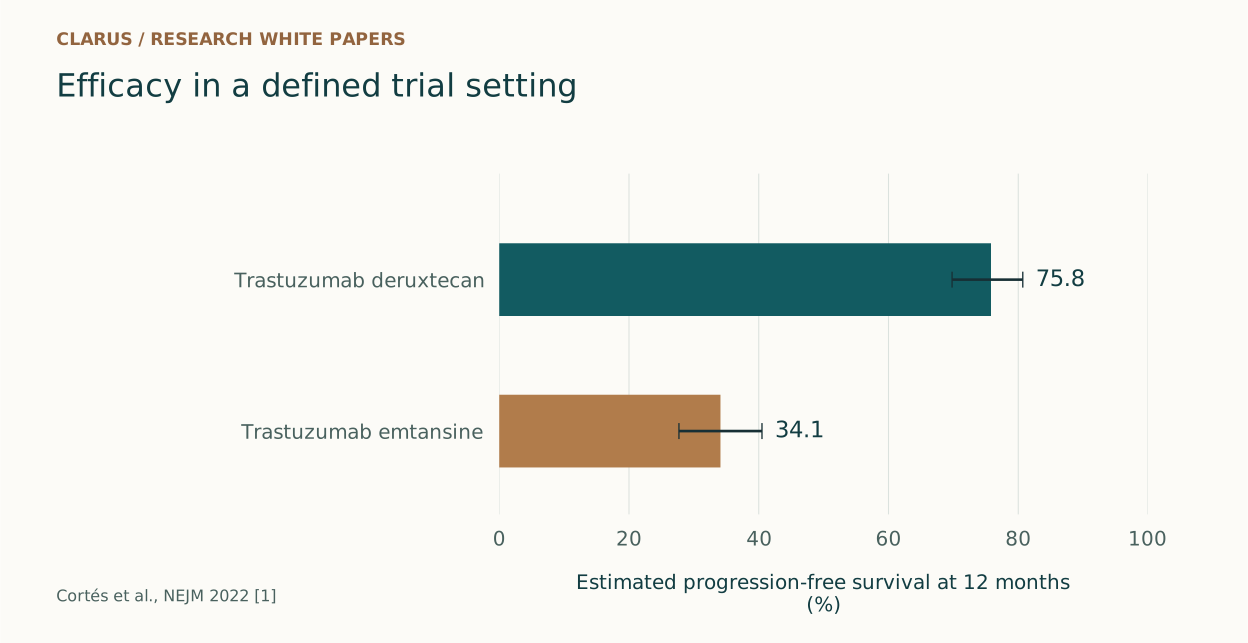
A randomized breast-cancer trial shows why efficacy and adverse-event context belong in the same product discussion.
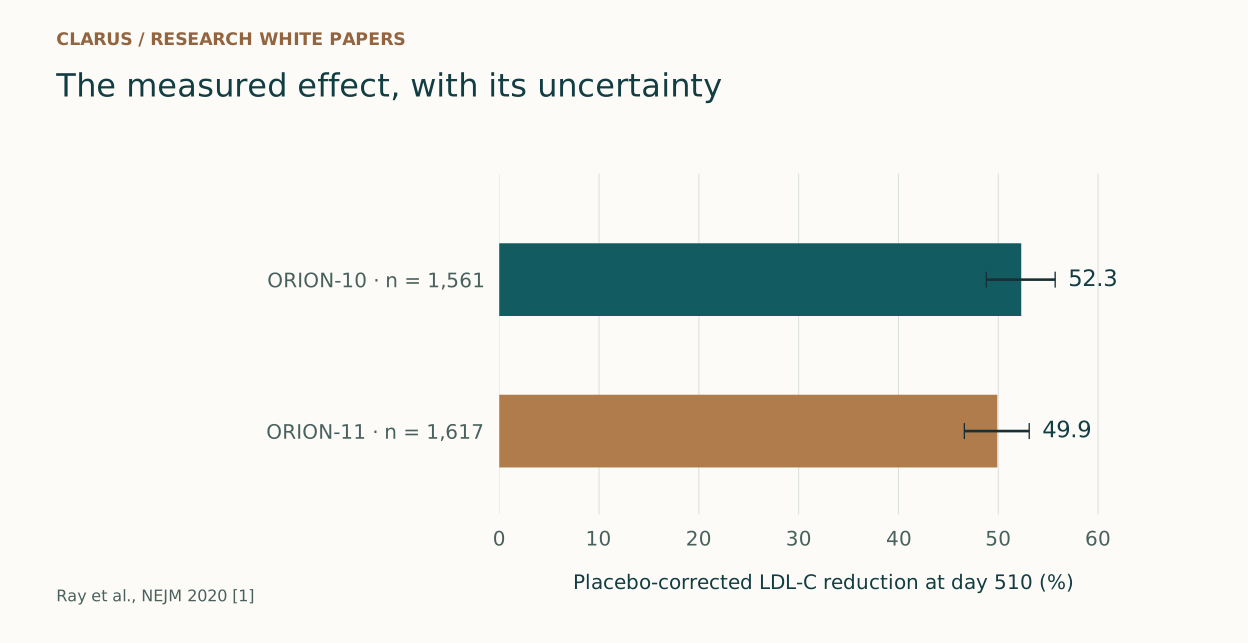
Two randomized trials illustrate how to communicate a strong biomarker result without extending it beyond the measured outcome.
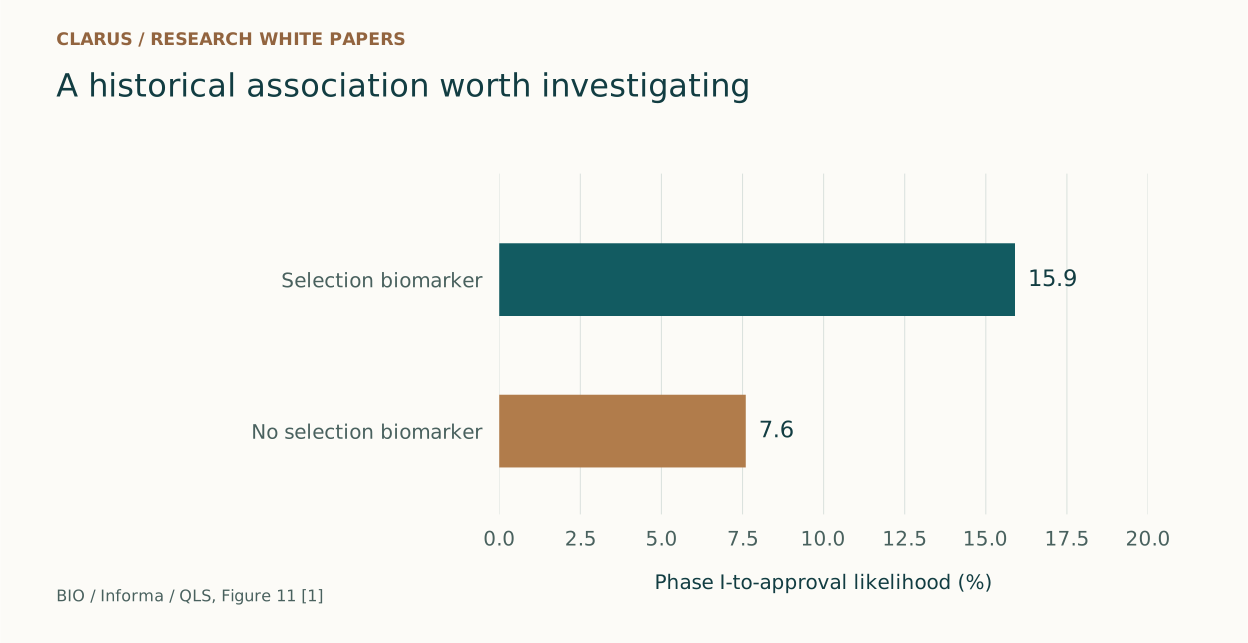
Historical industry data support careful study of biomarker-led programs while leaving important causal and operational questions open.
An oncology cohort shows why regulatory status and demonstrated patient benefit need separate tracking.
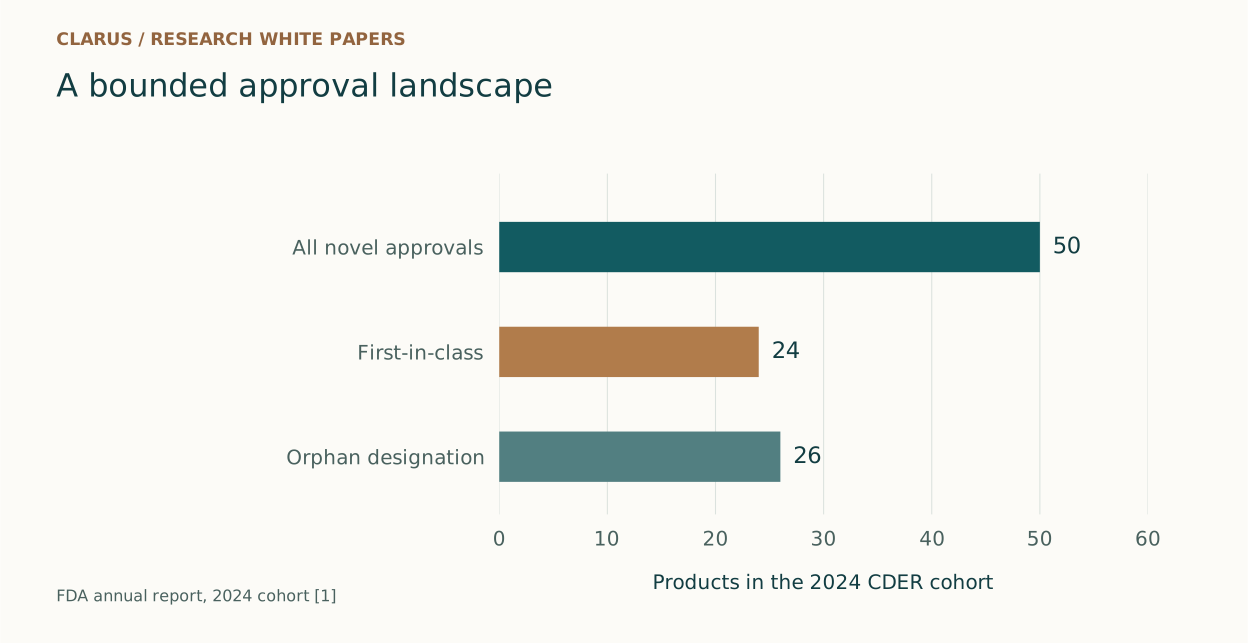
A defined FDA approval cohort can reveal the shape of innovation. It cannot rank clinical value or predict the next development program.

The 2016 hybrid system ties sensor, algorithm, pump, user tasks, and clinical evidence together.

HERALD and the 2021 rolling-review withdrawal illustrate a portfolio decision after an incomplete success.

The 2023 decision puts a measurable boundary around a broad molecular-platform narrative.

Dendreon’s 2010–2014 record separates clinical value, operating revenue, and financing resilience.

A historical storage change shows why a process convenience needs product-specific supporting data.

The 2018 contraceptive-ring program separates duration, pregnancy outcomes, and real-world handling.

The 2006 first-in-human event makes safety accountability an operating requirement.

An EGFR-selected trial demonstrates why population definition belongs in the clinical and access model.

APOLLO joined a molecular mechanism to 18-month clinical measures in a defined hereditary disease.

The 2014 record connects a diagnostic metric to false positives, follow-up, and completed care.

Pfizer’s 2007 exit makes adoption testing and reversible deployment financially concrete.

The 2021–2024 sequence connects authorization, pricing, coverage, and the cost of stopping.

The original G551D program shows how a focused evidence package can make a decision consequential.

The CMS access model makes outcome contracting, treatment logistics, and follow-up separate milestones.

The original 2014 authorization illustrates how a delivery route adds screening and monitoring dependencies.

A 2020 trial shows why recovery time, mortality, and hospital economics require separate interpretations.